 Fred is a 40-year-old firefighter who has been working as a first responder for more than 15 years. In his first year as a firefighter, he arrived at a car accident in which three children were killed. Since then, he has been among the first to respond to the scenes of countless injuries and dozens of deaths.
Although he tries not to think about the fatalities, he remembers each one. When asked how he and his colleagues cope with the trauma of witnessing such horrific events, he looks away, chuckles, and says, shaking his head, “We joke around and pretend it doesn’t bother us. You don’t want to be the one going to counseling. Everyone would call you a wimp.”
First responders such as firefighters, EMTs, and police officers face horrors in their work that most of us can’t imagine. In helping everyday people in the worst of times, they witness death, destruction, and much of the worst of what humans can do to hurt one another. A recent article from The Police Chief discusses the importance of seeking professional help for law enforcement officers. Physicians, physician’s assistants, nurse practitioners, nurses, and other medical professionals are also typically exposed to more human suffering than anyone should have to see.
The Boston Globe published an article a few months after the Boston Marathon bombings. It describes the experiences of several first responders whose lives were irrevocably changed by what happened that day. And this article in Counseling Today, aptly titled “First to Respond, Last to Seek Help,” lists the effects of traumatic experiences on first responders and the many barriers to seeking help these individuals face.
[fat_widget_trauma_ptsd_right]
Christine, 35, has been a hospital nurse in a children’s cancer unit for 10 years. While she can tell joyful stories of the children whose treatment succeeds in overcoming the cancer cells, there are many stories she doesn’t share. While she doesn’t speak about the pain and suffering she has seen, these memories haunt her at night when she tries to sleep. She is beginning to question her faith as she struggles to understand why children and their families have to experience such pain. Most days she cries in her car on the way to work, but she can’t stand the thought of leaving her job. Her supervisor has suggested she go to counseling and she views this recommendation as an insult to her professional skills.
Part of the problem is the environment in which firefighters, EMTs, police, and medical personnel do their heroic work. The fast-paced nature of their work settings limits opportunity for expressing feelings about what they see. Maintaining a clinical distance between patients and themselves helps first responders and medical professionals maintain their composure in the worst situations.
But there is a reason those of us who are helpers seek out helping work. We are caring people by nature, and it hurts to see others in pain. While most employers offer counseling through employee assistance programs, first responders and health care providers often feel, as Fred mentioned, that asking for help is a sign of weakness.
Exposure to trauma is an occupational hazard for first responders and medical professionals, and as such, it is necessary to practice self-care and know the signs that trauma is taking a toll. According to the Trauma Center of the Justice Resource Institute, the effects of exposure to trauma are cumulative. The longer one has worked as a first responder, the more likely he or she is to have a reaction to trauma.
What You Can Do about It
There are several great books available to help people who have experienced trauma firsthand. Two I recommend are Trauma Stewardship by Laura van Dernoot Lipsky and Compassion Fatigue by Charles Figley. Taking time away from work and seeking social support can be helpful. If needed, find a therapist or counselor who is specially trained in trauma to help you recover.
When to Consider Seeking Professional Help
According to the Trauma Center at the Justice Resource Institute, a first responder who is experiencing the following symptoms should seek professional help to assess and treat the effects of their traumatic experiences:
- Hyper-arousal: anxiety, trouble sleeping, fear, irritability, or anger, as well as other physiological symptoms of arousal of the parasympathetic nervous system.
- Avoidance: avoiding reminders of the traumatic event, including people who witnessed it, the place where the event occurred, thinking or talking about the experience, and/or avoiding other people—withdrawing from others and isolating oneself.
- Intrusions: nightmares, flashbacks, or other intrusive thoughts or memories of the event.
- Psychic numbing: using substances to avoid feelings, feeling numb, spacing out, or feeling as if things are unreal.
If trauma symptoms are interfering with your enjoyment of things you used to love, if you’re starting to hate your job and question why you went into the field, or if the way you look at the world has changed, counseling can help. Asking for help is a sign of strength.
References:
- First responders and traumatic events: normal distress and stress disorders. (n.d.) Retrieved from http://www.traumacenter.org/resources/pdf_files/First_Responders.pdf
- Gupton, H.M., et al. Support and Sustain: Psychological Intervention for Law Enforcement Personnel. The Police Chief 78 (August 2011): 92–97.
- Shallcross, L. (2013, August 1). First to respond, last to seek help. Counseling Today. Retrieved from http://ct.counseling.org/2013/08/first-to-respond-last-to-seek-help/
 When people think of eye movement desensitization and reprocessing (EMDR) therapy, they generally think about a treatment for trauma, which is partially accurate. Treating trauma is what EMDR therapy was developed for and continues to do. But since its development and introduction over 25 years ago, it has become more than an intervention and is now a comprehensive psychotherapy, one that is exceptionally effective in addressing multiple issues and challenges.
A common misconception is that a person has to be struggling with mental health or major life challenges to benefit from EMDR. On the contrary, one of the most interesting and innovative uses of EMDR has been in performance enhancement in addition to its ability to decrease fear, stress, or anxiety related to performance.
How EMDR Works
In short, EMDR therapy accesses and links the multiple facets of memory (image, cognition, emotion, and sensation) and uses bilateral stimulation/dual-attention stimulus (eye movements or tactile or auditory stimulation) in order to decrease disturbance associated with specific incidents in a person’s life. It taps into the brain’s natural ability to heal and helps it file away memory appropriately so that when the memory is recalled, there is no disturbance associated with the memory.
[fat_widget_right]
Other Ways EMDR Can Help
EMDR has several wonderful applications. In addition to decreasing disturbance associated with trauma, it is effective in decreasing anxiety and targeting irrational or negative thinking, both of which may get in the way of performance. In addition, it can help a person to gain confidence in his or her ability to perform a task or reach a goal. EMDR works to achieve this by installing positive beliefs, and by having a person imagine doing the thing he or she is nervous to do or wants to improve in while doing bilateral stimulation. This has the effect of simultaneously decreasing the fear, anxiety, or stress associated with the task and boosting confidence.
It seems that EMDR helps the brain to think in a healthier, more adaptive way by removing blocks (such as negative self-beliefs) and helping the person to tap into his or her strengths.
An Example of EMDR in Practice
Sometimes EMDR is hard to conceptualize without a specific example. Here is a hypothetical one.
Alice wants to implement healthy habits into her life, so she has set a goal of exercising three times per week. However, she is self-conscious when she thinks of going to the gym. She worries about other gym members and trainers judging her.
She visits an EMDR therapist to help her reduce her anxiety and to boost her confidence in going to the gym. The therapist completes a thorough history and teaches her stabilization and calming skills to utilize between sessions and (if needed) during the desensitization phase. Once fully prepared for the next phase of EMDR therapy, Alice and her therapist assess and desensitize any past experiences that feel related to the current experience.
Once there is no longer any disturbance associated with past experiences, they then assess and target the current situations that are triggering for Alice. Specifically, Alice targets the image of the gym, the belief “I am not safe,” emotions (fear and insecurity), and body sensations associated with this target. They use bilateral stimulation and work through the target until no disturbance remains, Alice is able to fully believe the thought “I can keep myself safe,” and she no longer has any negative body sensations associated with the target.
Alice and her therapist then move to the next phase of EMDR therapy, during which future situations are targeted. During this phase, Alice plays a movie in her head, imagining herself packing her gym bag, getting in her car, driving to the gym, going into the gym, completing her workout successfully, and leaving the gym feeling a sense of accomplishment. Alice finds that when thinking about this scenario, she has some anxiety and another negative belief: “I am going to fail.”
Alice plays the movie through several times, all while the therapist provides bilateral stimulation. If Alice finds she gets stuck, she lets the therapist know and the therapist helps her to work through the sticking points. She finds that each time she plays the movie in her mind, she is less anxious and more confident in her ability to go through the actions she is imagining. She eventually finds that she no longer believes she will fail and, while playing the movie the last few times, instead holds the belief “I am strong and capable.”
The next time Alice goes through the actions of preparing for and going to the gym, she has far less anxiety and much more confidence.
Of course, every case and person is different, but this is a simple example of how EMDR may be helpful in not only addressing past and present issues related to performance, but also in enhancing future performance and decreasing anxiety related to potentially triggering situations. The number of sessions will vary from person to person, but it has been my experience as a therapist that EMDR is both efficient and effective. Contact a therapist trained in EMDR if you think it might be beneficial for you.
Thank you for your question. Boy, oh boy were you put through the wringer. My heart ached to read of your experiences. I suppose the short version of my answer would be to see a therapist soon as you can, if only for the reason that you mention suicidality from your teens and depression today. This is not to be alarmist, but depression is something you don’t want to go unaddressed for long, more a sign of trauma than any “character issues.”
Clearly, your mother’s traumatic flight and your dad’s withdrawal left psychological scars that now need attending. This is not to blame anyone; the tragedy of mental health issues (you mentioned your father’s depression) is that those afflicted often end up passing on their condition by creating, as the authority figure in the home, a psychological mood or atmosphere of depression, anxiety, etc., which children are liable to absorb. They don’t call them the “formative years” for nothing. These wounds are passed along from generation to generation until someone has the courage to say “enough” and get some professional help. The good news is that you are young and in an excellent position to get help, and in so doing, start life over again and find contentment and purposeful living. Your experience, believe it or not, can be a vehicle for compassion and empathy for others down the road.
I am a fan of author and psychoanalyst George Atwood, who says in his excellent book The Abyss of Madness that, to paraphrase, people become depressed when depressing things happen to them. There are so many ways in which your trauma would upend anyone’s psyche. The most common question people ask me is, “Is this normal?” I usually say I gave up on normal a long time ago. Also, we therapists can relate to the childhoods and suffering of the people we work with more than we sometimes let on.
[fat_widget_left]
Yet another wounding occurs when the abandonment pain is not acknowledged or permitted to “exist.” A depressed parent may withdraw for self-protection and neglect the child, who cannot help but take it personally. Of course, as a young adult you now want to drink alcohol and blot it all out. What happened was wounding indeed, but not only were you alone with the abandonment, but you also had no one to even acknowledge or help you cope with its scarring legacy. Thus you were in the impossible situation in that you couldn’t have or not have these feelings; the terrible loneliness you experienced was compounded by not having a caring witness to empathize and help bear your very understandable feelings—a kind of solitary confinement.
You sound like a psychologically resilient person who survived a very difficult upbringing, who cares enough to do something about it now. I would encourage you look for a therapist who understands the kind of trauma you experienced, someone who is willing to be patient with you as these injuries to selfhood—which, actually, you seem to have borne quite nobly or you wouldn’t even be writing—begin to heal. Consuming vast quantities of drink or drugs is understandably tempting, but I encourage you not to. In the end, it will only erode your self-esteem and, in a sense, repeat the abuse by neglecting the hurt that needs a safe place for healing. You’re worth the effort (even if it doesn’t always feel like it). Thanks again for writing.
All my best,
Darren
 I find myself looking at this person; I feel for him, knowing that he is tormented by his anxiety and sense of isolation. While he has made amazing strides in therapy, especially through eye movement desensitization and reprocessing (EMDR), there is something that keeps “blocking” him from reaching the point of accepting that the past is truly “over.” There is something that pulls at him, drags him down into the murky depths of his sadness, telling him that he can’t reach that positive belief that he is “good enough.”
His story is not unique. He is like many of the people I work with in therapy who struggle to loosen themselves from the hold of trauma. He is like many who walk into my office wanting to feel free of the past, to fully integrate what they know “logically”—that they are “OK, lovable, worthy, safe, here now”—with their emotional selves, who are just not buying it.
As you are reading this, perhaps there is some aspect of your healing work that you feel “stuck” in. It’s a common theme; folks do amazing trauma healing work and perhaps might find that they have hit a wall. They want to feel healed, but on some level it just won’t budge. “I don’t know why” is a common statement. What we often find is that there is some next layer of the person’s experience that is revealing itself. In EMDR therapy, we call it a “blocking belief.”
[fat_widget_right]
Why does this happen? Why is it that, on the one hand, we can know that the past is behind us, and yet there is also a sense that it is not? We can begin to explore this question not only through the perspective of trauma therapy, but specifically EMDR therapy.
A blocking belief essentially blocks us from shifting our core beliefs about ourselves. For example, in processing deep-rooted trauma through EMDR therapy, the person I described was working through a core belief (EMDR therapists call it a “negative cognition”) of “I’m not good enough” and then, right when it was getting to a decreased intensity, found another layer—a blocking belief that “I shouldn’t get over this.” That same blocking belief kept the trauma from decreasing in intensity from a 10 (most disturbance) to a zero (neutral/no disturbance). It wasn’t until we shifted that blocking belief—“I shouldn’t get over this”—that the core belief of “I’m not good enough” could release its hold as the trauma was processed.
Blocking beliefs can come up often in EMDR therapy when we ask about the SUDs (subjective units of disturbance scale). It’s a scale we use to find out how the person’s distress about the event has shifted. Keep in mind that it doesn’t mean that the event is not disturbing. That it’s disturbing doesn’t change. It will be a disturbing event as a trauma, by its nature of being a trauma. But the person doesn’t have to continue to feel disturbed by it.
When we start to explore our core beliefs about ourselves, and the traumas that have driven them, be sure to explore any blocking beliefs that may show up. It may just mean that you are that much closer to healing those traumas than you may have thought. It may just be that deepest layer waiting for you to discover it.
Believe it or not, it is possible to get to a neutral or zero about traumatic events and the disturbance we feel about them, even for the most upsetting and distressing experiences. But there may be some reason we hold on. Unconsciously, perhaps we think we need to keep some fear, just enough, to help us feel safe and prepared for next time. Perhaps we think it’s “impossible” to heal from those experiences. Perhaps there’s a mistaken, unconscious belief that it’s not “something we should get over,” that it’s not OK that we heal this event: “It’s just too painful; if I feel neutral or no disturbance, then I am not honoring the experience(s) and the impact on my life.”
The fact is, and this comes up a lot for folks when they do EMDR, it is possible to heal trauma.
It is possible to feel differently about our lives, whether it be to feel safe, calm, or even feel and know that the past is over. Yes, it can change; I’ve seen it. I’ve also experienced it. That said, it can take time, even with EMDR therapy, especially with multiple of types of traumas, and when traumas span across the developmental stages of our lives.
 Trauma often leaves us living in a seemingly hostile world, feeling ineffective, believing that help cannot be expected.
To some degree, the concept of limited internal power and limitless external power remains an essential component of complex trauma. Fatalism (or “learned helplessness”) is a debilitating side effect of experienced oppression. In many, the freeze response includes disengagement from life—an intentional separation from anger, power, and movement.
Internalized Oppression and the Freeze Response
The human body has a few options when threat is detected. If we look around and find physical signals of safety from another, our anxiety recedes. If support is not available, we move into fight-or-flight mode, mobilizing for self-protection. Especially for children—when physical size renders fight useless and dependence precedes flight—freeze is the next step.
Like fight or flight, freeze is a biological resource. It serves a purpose. It effectively preserves within our core what we deem most fragile and valuable, as if moving into hibernation or hiding in a safe until safety once again presents itself. We lie dormant.
While the mechanism is an effective one, the experience of life in a freeze state is not always pleasant. We still access fight and flight, often more readily than others, as if we are living on the border of that biological response. In fact, we are. As freeze is a drop after fight or flight, the experience of fight/flight becomes the wall between us and the world. Life itself becomes a protected bubble, with little action—sometimes indiscernible movement. Just breathing. Waiting. Sometimes minutes. Sometimes decades.
We live on as a sliver of our whole: eating food, maintaining, avoiding any risks that might bring us closer to whatever dreams we hold. We may carry some fantasy of being recognized or saved one day, or eventually finding courage and overcoming our self-imposed prisons. One major challenge lies in the fact the only route to freedom includes a journey through the impenetrable panic of fight/flight, and we still carry the template of our last experience there. So we end up living—or at least maintaining—in cages of our own making, feeling frustrated, depressed, powerless to escape or change.
This is a form of internalized oppression. On a macro scale, internalized oppression (also known as self-directed oppression) is when a marginalized or oppressed population begins to accept and act on stereotypes and other inaccurate beliefs related to it. On a personal level, internalized oppression happens when we impose limits on ourselves in pursuit of safety.
This is a form of internalized oppression. On a macro scale, internalized oppression (also known as self-directed oppression) is when a marginalized or oppressed population begins to accept and act on stereotypes and other inaccurate beliefs related to it. On a personal level, internalized oppression happens when we impose limits on ourselves in pursuit of safety.
Noticing Our Power
Many of us have seen the violence of power and want no part of it. We divorce from power within ourselves. We feel weak and, at the same time, fear our strength.
When we look from a distance, we see violence and oppression at a global scale. Zooming in, it becomes apparent between cultures and classes. Then, in the family unit, violence presents as abuse (physical, sexual, verbal, etc.) or neglect. Using therapeutic models such as Hakomi therapy or Internal Family Systems, we zoom in still further, witnessing the pain and “stuckness” of internal conflict and oppression.
In simple moments—maybe sitting in a garden or a counseling office—we recognize the power in ourselves. We recognize a conflict as we feel the physical sensation of shifting our awareness between the part that judges/contains and the part being contained. We notice the part contained using anger as a resource to build power, to break our own walls. We realize how dependable and valuable our own containment system has been, and may even feel gratitude noticing that part of ourselves valued us so completely. Maybe we feel the contained part in our throat, moving upward, while the other part—the tension in our shoulders—acts as the dam that holds back forbidden parts of ourselves: the precious and preserved parts.
Leaving the Island
Much like Tom Hanks in the film Cast Away, the island serves as a metaphor for our own self-containment. It is isolating, endlessly frustrating, lonely, and safe. It is a place one could live out a lifetime in the experience of nothingness. The only escape represents potential death … and simple change: the unknown. This is the experience of the freeze state. A giant ocean lies between you and the world, with no direction or guarantee of reaching that life of which you dream.
Reminders, Tips, and Tricks for Overcoming Internalized Oppression
- Anger is a resource.
- Get to know, feel, understand, and trust your body.
- If your head needs information in order to let down its guard, explore some of the leading research in trauma and complex trauma. Peter Levine. Bessel van der Kolk. Pat Ogden.
- Start living in your body—moving away from the judging, analyzing, and planning of your head.
- Take in the feeling of movement. Google “walking meditation.” Explore yoga.
- Take in the good. When things are going well, when you reach a goal, sit and feel your body.
You may notice a sense of overwhelm in considering reaching out for help for internalized oppression. I often recommend simple self-compassion and permission to take things slow. This is gradual exposure to life, building tolerance for change. Even two minutes at a time can help. Consider support groups or one-on-one counseling with a specialist in complex trauma, childhood abuse, or learned helplessness.
 When soldiers are killed in battle, families grieve and nations mourn for some of their bravest citizens. However, wars claim thousands of lives even decades after agreements have been reached and treaties are signed. According to the U.S. Department of Veterans Affairs (VA), approximately 22 military veterans commit suicide each day in the United States. While physical injuries obtained during military service are often immediately addressed, deep psychological wounds may go untreated for years—silently festering into suicidal ideation or other mental health issues.
Mental toughness is a highly valued trait in the military. Fresh military recruits train for months to toughen themselves physically and mentally because combat situations expose soldiers to many traumatic events such as being shot at, seeing a friend get shot, or seeing death up close and personal.
Despite their diligent efforts to prepare, some soldiers are not able to cope with the intense trauma they may encounter in combat. As a result, they can become severely scarred emotionally and psychologically. With mental injuries left unaddressed or simply ignored, many military veterans discover that going home may be even more difficult than going to war.
Military Suicide Rates
Veteran suicide statistics obtained from the Department of Veterans Affairs indicate that a veteran commits suicide approximately every 65 minutes. This rate translates to over 8000 suicides per year. And as astounding as these figures are, they are likely underestimated. The data used to determine the high rate of veteran suicide in the U.S. has been challenged numerous times as it was obtained from residents of only 21 of 50 American states. Some of the largest states with high veteran populations, including California and Texas, were not included in the Department of Veterans Affairs’ report on military suicide rates.
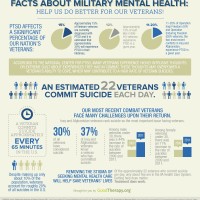
Suicide rates among veterans are much higher than those among American civilians. Approximately 20% of all suicides in the U.S. are committed by current or former military personnel, despite the fact that veterans make up only 10% of the population.
While resources for treating posttraumatic stress (PTSD), depression, and other hallmark psychological injuries are available, only 56% of qualified Operation Enduring Freedom/Operation Iraqi Freedom (OEF/OIF) veterans make use of them (2013). Similarly, of the reported 22 veterans who commit suicide each day, only 5 are in the Veterans Affairs Health Care system.
The good news is that we know when veterans do get help, it makes a difference. In 2007, the Veterans Health Administration launched an intensive suicide prevention effort and has since reported a decrease in:
- Overall rates of suicide among veterans with mental health conditions.
- Rates of suicide in the 12 months following a survived suicide attempt among veterans.
- Rates of suicide for veterans ages 35-64, which is one of the highest risk groups.
- An overall decrease in non-fatal suicide attempts.
The Stigma of Mental Health Care in the Military
Mental health issues and the receipt of mental health care treatment can be highly stigmatized within the military. The military promotes ideals such as self-sufficiency, endurance, mental fortitude, and strength, values that also support the notion—however unfair—that those seeking mental health treatment are deficient, dependent, or weak.
Factors that significantly affect service members’ decisions to seek mental health treatment may include:
- How higher-ranking officers and non-commissioned officers talk about mental health treatment.
- The belief that seeking mental health treatment will have negative repercussions on a service member or veteran’s career.
- The gender of the service member or veteran.
- The marital status of a service member or veteran.
- His or her military occupational specialty (MOS).
- Public expectations of how service members and veterans are supposed to cope with trauma.
Stigmas surrounding mental health treatment, both in the military and outside of it, greatly reduce the number of at-risk veterans that will seek treatment. Lisa Danylchuk, EdM, LMFT, E-RYT, an Oakland, California-based therapist and posttraumatic stress Topic Expert, believes, “Stigmas like these can increase feelings of shame and isolation, which can increase feelings of depression and decrease the likelihood that a depressed or suicidal person will reach out for help.”
In addition to these social pressures, veterans may believe that seeking treatment goes against their core principles and will damage their very identity.
Mental Health Issues Veterans Face When They Come Home
The Department of Veterans Affairs posits that posttraumatic stress, anxiety, depression, bipolar tendencies, and substance abuse are among the most common mental health issues affecting veterans of OEF and OIF.
When members of the armed forces return home, they often experience difficulties with reintegration. The 2014 Iraq and Afghanistan Veterans of America (IAVA) Member Survey states that loss of identity and mental health concerns were two of the top three challenges service members faced when transitioning out of the military. Of the 2,089 Iraq and Afghanistan combat veterans who completed the survey, 53% reported having a mental health injury.
Traumatic brain injury (TBI) is another health concern for veterans that has received much attention from the medical community in recent years, due primarily to the high number of OEF and OIF veterans who have endured blasts and injuries to the head and returned home with symptoms of TBI.
TBI may occur as the result of striking the head with an object, hitting the head during a fall, or, as is usually the case with combat veterans, the head being affected by a nearby blast or explosion. TBI can result in numerous health concerns, including emotional, behavioral, cognitive, and physical deficits. Records indicate that 18% of IAVA Member Survey responders were diagnosed with traumatic brain injury and have reported an increase in anger as well as changes in their personality.
Depression and anxiety are also major concerns for veterans. The Anxiety and Depression Association of America explains that veterans may feel out of sync with family and friends, but they should try to avoid social isolation. When veterans are cut off from social support, depressed thoughts may quickly lead to suicidal ideation. According to the IAVA Member Survey, 31% of Iraq and Afghanistan veterans have contemplated taking their own life since joining the military, compared to only 6% prior to joining.
Veteran Mental Health Resources
Though many veterans will experience their greatest mental health struggle after combat, in recent years, a number of mental health services and programs have been established specifically to aid military veterans. Many services within the VA Health Care system are free of charge, and many local mental health professionals and agencies offer their expertise at a reduced cost to veterans. If you are a current or former service member experiencing mental health issues, please reach out to these available resources for assistance:
- Call the Veterans Crisis Line at 988. Press 1 to speak to a Department of Veterans Affairs responder. People reaching out for assistance can also chat online or send a text message to 838255. Loved ones of veterans are encouraged to use the crisis line too.[fat_widget_right]
- Enroll in and obtain VA Health Care, which provides access to numerous mental health services at affordable rates or free of charge depending on the veteran’s economic and discharge status.
- Participate in regular post-deployment screenings that attempt to assess the mental health of military personnel after their service and encourage fellow veterans to do the same. These post-deployment screenings are designed to identify risk factors and gather data to help other veterans.
- Seek a qualified local therapist who can offer personalized care. Many therapists have specialized training to help those experiencing PTSD.
- Reach out to local support groups and veteran service organizations. Support from fellow veterans can aid in successful mental health treatment.
Family members and friends can also help veterans cope with their psychological wounds. Danylchuk encourages veterans to seek mental and emotional support not only professionally, but also within their social circles. Danylchuk recommends to friends and family members of veterans, “Listen with a non-judgmental ear, but don’t push someone to talk about something they are not ready to share. Encourage mindfulness practices like yoga, meditation, tai chi, and qigong. Remind veterans that they are having a normal reaction to an extreme experience, and that their experiences of anxiety, depression, and/or PTSD do not mean something negative about them; it just means they are still processing parts of their experience.”
References:
- Anxiety and Depression Association of America. (n.d.). Tips for soldiers and veterans. Retrieved November 15, 2014, from http://www.adaa.org/living-with-anxiety/military-military-families/tips-soldiers-and-veterans
- Bagalman, E. (2013). Mental disorders among OEF/OIF veterans using VA health care: Facts and figures. Retrieved from http://fas.org/sgp/crs/misc/R41921.pdf
- Iraq and Afghanistan Veterans of America. (2014). 2014 IAVA member survey. Retrieved from http://media.iava.org/IAVA_Member_Survey_2014.pdf
- Kemp, J., & Bossarte, R. ( 2012 ). Suicide data report, 2012. Retrieved from http://www.va.gov/opa/docs/suicide-data-report-2012-final.pdf
- Miggantz, E. L. (2014). Stigma of mental health care in the military. Retrieved from http://www.med.navy.mil/sites/nmcsd/nccosc/healthProfessionalsV2/reports/Documents/Stigma%20White%20Paper.pdf
- United States Department of Veterans Affairs, Employee Education System. (2010). Traumatic brain injury. Retrieved from http://www.publichealth.va.gov/docs/vhi/traumatic-brain-injury-vhi.pdf
- United States Department of Veterans Affairs. (2011). VA suicide prevention program. Retrieved from http://www.goyourownway.org/GOYOUROWNWAY/DOCUMENTS/VETERANS/VA%20Suicide%20Prevention%20Fact%20Sheet.pdf
- United States Department of Veterans Affairs. (2014). How common is PTSD? Retrieved November 15, 2014, from http://www.ptsd.va.gov/public/PTSD-overview/basics/how-common-is-ptsd.asp
- United States Department of Veterans Affairs. (2014). Polytrauma/TBI system of care. Retrieved November 15, 2014, from http://www.polytrauma.va.gov/understanding-tbi/
 Do you want to build a case about how your partner is wrong and defective or do you want to repair the relationship? So many people come to my office wanting to convince me how wrong and/or bad their partners are. They are so busy focused on their partners’ flaws that they don’t pause to look at themselves and what their part in the relationship might be.
A version of the Serenity Prayer that I like is:
God grant me the serenity to accept the people I can’t change,
The courage to change the one that I can,
And the wisdom to know that is me.
Emotional hurts or traumas experienced in early childhood—we’ve all been there to greater or lesser degrees—stay with us, but they can be overcome. Our opinions of ourselves and others are formed by these early experiences. These are what become familiar. Unconsciously, we are seeking the comfort of the familiar even though it may not be good for us. Often we deny and overlook these early experiences, as we don’t want to remember the hurt and bad feelings.
Unconsciously, we attract partners who feel familiar, and often they are more similar to our most unresolved relationship from childhood. Most of us aren’t consciously aware that this is what is happening.
[fat_widget_relationships_right]
So how does all this happen?
I maintain that the best individual therapy happens in the context of couples therapy, where each partner holds up a mirror of sorts for the other, giving each partner the opportunity to see themselves more clearly. When we don’t like what we see, it becomes easier to blame our partners and point out that they are flawed. Bringing up these old feelings and looking at ourselves takes courage.
Rather than saying, “You did this or that wrong and therefore you are (insert negative label here),” we can focus on ourselves and what is going on within us.
It is helpful to say:
- “When (whatever the situation that has caused upset) happens, I feel _______.” Ask yourself what your primary emotion is. Sometimes we think we are angry, but we may actually feel hurt, with anger as a secondary emotion. Try to identify your primary emotion. If someone scared me, I could get angry that they did this, but fear would be the primary emotion.
- “What this reminds me of from childhood is _______.” Now you start to become aware of your childhood wounds and disappointments. As the old saying goes, if you can feel it, you can heal it. Don’t take too much time to figure this out; just notice the first thing that pops up—it’s usually the correct response.
- “What I tend to do when I feel this way is _______.” Your response is likely to be what you did when you were a child to protect and defend yourself. It worked for you then, and you think it will work for you now, but it might not.
- “I react this way to hide my fear of _______.” This is when you are likely to feel vulnerable, but it is the vulnerability that leads to intimacy. We all have fears, and we need to identify them so we can work to alleviate them at a conscious level. When we don’t, we tend to act them out defensively in an unconscious way. Once they are identified and labeled, we are better able to make conscious choices as to how we respond.
- “What I want and need is _______.” What was it that you wanted and needed in childhood that you didn’t get? It is likely the same as or similar to what you want from your partner, but you might not even be conscious of wanting this from him or her.
- And finally, to your partner: “Would you please _______?” Our emotional brain heals through experience. When we experience receiving what we truly need, we begin to heal. Hopefully, you have a partner who will do this for you, just as you would be willing to do it for him or her.
Emotional intimacy involves two people entering into a conscious relationship with an agreement to support each other in healing their childhood wounds. When we do this, we evolve into mature individuals and have healthier relationships. We are then able to blossom into expressing the fullness of who we are as individuals. A relationship at this level is an example of an interdependent relationship. The more the old issues resolve, the more enjoyable a relationship will become.
 If you were to attend a professional training on trauma, the instructor would likely reference the nervous system and its window of tolerance. In recent years, trauma researchers and therapists have developed a deeper understanding of the nervous system’s role in regulating extreme stress, and have learned some techniques for regulating this system.
You have probably heard of the fight-or-flight response, which describes our impulse to defend ourselves or run until we reach safety. This is part of the window-of-tolerance model, but it’s not quite the whole picture. Let’s start with understanding a regulated nervous system.
A regulated nervous system experiences a stress and calming response throughout the course of a given day. Perhaps you are driving and someone brakes unexpectedly ahead of you; when your nervous system is regulated you will feel some stress, but once your body feels safe and you are able to act in a way to ensure your safety (i.e., press your own brakes), your system will calm back to baseline. Dr. Dan Siegel of UCLA coined the term “window of tolerance” to describe this space in which we can regulate ourselves without too much effort.
Make sense? You’ve probably felt some of these fluctuations in your system today—rushing to get somewhere and relaxing when you arrive on time, for example. Next we’ll explore what happens to the nervous system when a traumatic experience enters the picture.
[fat_widget_trauma_ptsd_right]
Trauma pushes the activation of the nervous system beyond its ability to self-regulate. When a stressful experience pushes the system beyond its limits, it can become stuck on “on.” When a system is overstimulated like this, we can experience anxiety, panic, anger, hyperactivity, and restlessness. This is the fight-or-flight mode; your body is activated and ready to move.
Some nervous systems will stay here, while others will dip below the normal range and become stuck on “off.” Below the window of tolerance we see symptoms of depression, fatigue, disconnection, and lethargy. Systems can get stuck above or below the line for prolonged periods of time, or they can vacillate between the two.
How can you discharge the traumatic stress and transition back into the window of the regulated nervous system? Here are a few tips:
- Seek safe relationships. Being with someone who is safe and soothing will help your nervous system settle and create a safe space for you to connect and share your experience. We are social beings and we heal in relationship, so if you find yourself isolating or pulling away from social contact, consider instead seeking out people who feel supportive.
- Practice mindful breathing. This trauma response is connected to the brain stem (basic physiological regulation) and the limbic (emotional) brain. Practicing mindful breathing helps connect a basic physiological process (breathing) with your prefrontal cortex (thinking brain), which helps integrate and shift our neurological state. To put that more simply: breathing has a HUGE capacity to calm the brain and regulate the nervous system.
- Find a therapist who understands trauma and can help you get to know the habits of your nervous system. Recognizing when you are outside of your own window of tolerance and building personal strategies to soothe or stimulate your system is key to regulating in an ongoing way. For some people, sitting still is calming; for others, movement brings more peace. Find someone who can support you as you explore what works best for you.
There are many unique and healthy ways you can learn to support your nervous system and bring it back into its window of tolerance when something stressful occurs. Creating a support network that includes a trained trauma therapist is a helpful way to build your ability to heal and recover from traumatic experiences. When you learn to work with your nervous system, you may even build up a wider window of tolerance, which can allow you to move about the world feeling more grounded and connected to others.
Have questions? Please post them in the comments section below!
Thanks for writing in. Gosh, I’m sorry you’ve been through such an emotionally brutal experience. I can’t imagine the blow of losing a girlfriend and an allegedly good friend at once, in this manner. It sounds like you had some suspicion that something was amiss, but when you asked your alleged friend directly, he lied.
I would not be surprised if you are experiencing some kind of posttraumatic stress from such an experience. Because relationships are so crucial to our sense of self and security in the world—especially intimate relationships—having our trust and emotional safety shattered in this way would naturally be extremely distressing and perhaps traumatic. Sleep, appetite, and other functionality is sometimes affected. Perhaps your other relationships are being affected, in terms of wondering who you can and can’t trust. Being lied to so baldly would completely scramble trust even in our own perceptions and sense of reality since what happened contradicts so dramatically what we thought we were seeing.
This may account for the self-blame on evidence in your question, when you “feel like an idiot” for trusting. That harsh self-condemnation is the result, I suspect, of trusting your own self-experience with people close to you—who often serve at least in part as reflections of ourselves, our sense of who we are and what we can have faith in—which, now shattered, leaves you with self-doubt over what you thought you were perceiving.
[fat_widget_relationships_left]
However, you are not responsible for the heinous behavior of these two. Taking you at your word (and I see no reason not to), I see no trace of any reason for them to have treated you so shabbily. I imagine this to be another reason for the self-doubt and self-condemnation you express, because our loved ones are often mirrors for us: when someone we trust and love treats us badly, a possible instinctive reaction is, “What am I, chopped liver?” It sounds like these two colluded in deception and abusive behavior, and of course such betrayal would be intensely injurious to anyone’s self-esteem.
Of course, being a therapist, I am going to suggest therapy in the spirit of seeing this episode as trauma. Often, such experiences will revive historical doubts and losses or previous crises of faith, if we have had other betrayals in the past. I think having a safe place to vent and process all kinds of understandable emotional reactions could be quite healing. Rage, grief, shock, hurt, and fear of future betrayals are but a handful of the normal human reactions you might be having, and the safe space of therapy can provide an outlet. You may need to vent about this over and over for a long time, and this is OK; don’t worry about “boring” the counselor or therapist. These losses take time to process and heal.
You might also want to look around for support groups, even online. Perhaps there is a group, either locally and in person or online, that offers support for those who have been betrayed in this way.
Finally, I wouldn’t be in a super hurry to start pressuring yourself, or feeling pressure from others, to “forgive and move on.” Forgiveness is a more complicated subject than meets the eye, and often presented in highly idealistic terms. In principle, of course, it is a beautiful thing. But people often rush to forgive others for hurts that aren’t fully understood or acknowledged, even by the injured person; superficial forgiveness may be espoused while hurts and resentments unconsciously simmer and continue to impact the personality—exploding when the person is re-traumatized in parallel ways.
I am not “against” forgiveness, of course, and find it ultimately to be liberating (and probably necessary in the long run). But it is not as neat and tidy as presented on bumper stickers and inspirational Facebook posts. There is a nice saying from Al-Anon: “Acceptance is not approval.” One can accept what has happened, without acting vengefully and in a spirit of moving forward, but there’s something to be said for learning from harmful behaviors (dishonesty, selfishness), remembering so as not to repeat them. Sometimes others show us what not to do.
Thanks for writing, and I wish you the best in your journey of healing. I hope you find a girlfriend and friend who treat you with the honesty and integrity you deserve. I suggest you treat yourself as a very good friend who is suffering, which is more consideration than you received, sadly, from the two who betrayed you.
Kind regards,
Darren
 Most people have had a traumatic experience of some kind. While many of us learn to cope and be resilient in the face of trauma, others may become overwhelmed.
Trauma is an overwhelming experience, and it is our experience and reaction, more than the event itself, that defines trauma. The Diagnostic and Statistical Manual of Mental Disorders criteria for posttraumatic stress (PTSD) are specific and involve being exposed to something that threatens life; however, different people have a range of responses to similar situations. What may feel mundane to you could be traumatic to me, and vice versa. No judgment here—we are all wired differently.
Below are three simple steps that can help anyone facing an overwhelming life experience—be it a natural disaster, loss of a loved one, an experience of violence, or an abusive past.
Once we’ve encountered a trauma, how do we get through it? [fat_widget_trauma_ptsd_right]
- Seek safety. The first step in addressing trauma is to create safety, on multiple levels. Physically, find a place to ground yourself and feel protected from harm. Then look for ways to actively nurture yourself. Think of a bird flying along and running into a glass window. What does that bird need—perhaps a little shoebox with some water and food, and loving hands and eyes to watch over it? On an emotional level, seek out those people in your life who can tend to you as you would that bird, who offer love, support, caring, and understanding. If you have a network of friends and family, call on them. There are also people and organizations out there to help, serve, and support you. Also, seek support on a spiritual level. Connecting with a higher power or deeper intelligence that resonates with you can be a saving grace. Many gravitate toward nature. Find what soothes your soul.
- Process. Once you feel more grounded, contained, and safe (and you feel READY for this step), you can begin to process the parts of the experience that are still with you. Look to your body and find the movement that helps you get in touch with yourself and your feelings. Find a good therapist or group in which you can talk openly and honestly. As you process, you’ll continue to develop coping skills and strengths and build upon the safety and containment you’ve created.
- Examine. When the bulk of your processing is over, life goes on. The goal is not to forget the traumatic experience but to resolve the emotional charge it holds in the present. Look at any learning or growth that has come from this experience. What insights have you gained? Make a note to yourself of any positive things you have learned that you can carry forward.
When we process one life event thoroughly, we may discover more there—other experiences or things we have learned about ourselves that deserve attention and healing. By now, hopefully, you have good relationships and supports you can lean on to continue your healing journey mindfully, with compassion for yourself and with the knowledge that efforts put toward healing will be helpful for you.
Disclaimer: It is never this neat. These steps will weave in and out of each other. Trauma, like life, can be chaotic, and healing is an art more than it is a science. Following your intuition and building a network of support will help. There is a way through; use these steps to guide you through your healing process.
 The first question a person who is seeking help for trauma often asks is, “Will I ever get better?” It is common to feel hopeless after experiencing a traumatic event. Trauma affects how the brain functions. It can physically change the brain and make people feel that they are not themselves any longer. Activities that were once simple and automatic become difficult or feel downright impossible. Fortunately, the options for the treatment of trauma are very effective.
There are several options when it comes to choosing a modality of trauma treatment; I’ll cover them in subsequent articles. Having information about each modality can help a person to make an informed choice when choosing the route of treatment that is right for him or her.
Eye movement desensitization and reprocessing (EMDR) is one effective method of treating trauma. The name of this intervention is a mouthful; just seeing or hearing it can cause a person to feel overwhelmed and confused. It is, in reality, a fairly simple intervention that addresses the many effects of trauma, including negative beliefs about the self (such as “I am not safe” or “I am bad”) that commonly arise, the sensory aspect, including images and body sensations related to the trauma, as well as emotions.
[fat_widget_trauma_ptsd_right]
According to the EMDR Institute, Inc., several studies have been conducted to test the efficacy of EMDR, and the data show that a majority of people experience a reduction in their trauma-related symptoms after treatment. One such study, conducted by Carlson et al. (1998), found that 77.7% of veterans who had experienced multiple traumatic events had an elimination of posttraumatic stress (PTSD) symptoms after participating in 12 sessions of EMDR. Another study, conducted by Arabia et al. (2011), found that people who had experienced a life-threatening health issue related to cardiac problems had a reduction in symptoms related to PTSD, depression, and anxiety.
Overview of EMDR Treatment
There are eight phases in EMDR treatment. Francine Shapiro (2001), who developed this therapeutic technique, states that it is important to understand that how long a person must spend in each phase will be different for each individual.
The phases include:
- Getting a history
- Preparing a person for the trauma work through building coping skills
- Determining the specific components of the first trauma that will be reprocessed
- Desensitization
- Installing a positive belief about the self when recalling the trauma
- Checking in with the body for any residual trauma (body scan)
- Closing of the session
- Reevaluation during the next session to see if any new information has come up or changes have happened between sessions
The Role of Dual Attention Stimulus
The thing that most people find fascinating or even strange about EMDR is what is called dual attention stimulus, which is utilized during the desensitization, installation, and body scan phases of EMDR. This involves either moving the eyes back and forth, tapping on one side of the body and then the other (i.e., left hand and then right hand), or using sounds in alternating ears.
The dual attention seems to do a few things: helps the brain to work through previously difficult material, makes recalling memory easier, and has a calming effect. It is unknown why the dual attention has this effect, but several studies support its effectiveness (EMDR Institute, 2011).
Dual attention can also help a person to keep the attention in the present while allowing the brain to go to the past, which can help to decrease the potential for hyperarousal, which could get in the way of treatment. It is also thought to help with moving information through the brain so it can be filed away correctly.
How EMDR Helps the Brain
Another way to see the EMDR process and how it helps is to imagine that your brain and its memory networks are a network of streams and rivers. When a traumatic event happens, it is almost like a beaver dam has been constructed somewhere within the network, which can send the entire network into panic mode. The water gets backed up and overflows, which can affect areas that don’t seem connected to the network with the block.
In the case of trauma, it is the emotion, memories, body sensations, thoughts, and beliefs that are overflowing and not getting where they need to go. EMDR’s main objective is to address and remove the beaver dam, or block, so that the brain can process. Removing blocks essentially helps the brain to tap into its own ability to heal itself.
Is It Right for You?
If interested in participating in EMDR therapy, make sure that the therapist you choose was trained by a reputable source.
EMDR is a well-researched and effective treatment for trauma on any level, no matter how small or big. Even if EMDR is not the right fit for you, other resources and treatment modalities are available.
References:
- Arabia, E., Manca, M.L., and Solomon, R.M. (2011). EMDR for survivors of life-threatening cardiac events: Results of a pilot study. Journal of EMDR Practice and Research, 5, pp. 2-13. Retrieved September 1, 2014 from http://www.emdr.com/general-information/research-overview.html
- Carlson, J., Chemtob, C.M., Rusnak, K., Hedlund, N.L, and Muraoka, M.Y. (1998). Eye movement desensitization and reprocessing (EMDR): Treatment for combat-related post-traumatic stress disorder. Journal of Traumatic Stress, 11, 3-24. Retrieved September 1, 2014 from http://www.emdr.com/general-information/research-overview.html
- EMDR Institute, Inc. Dual attention stimuli. Retrieved September 1, 2014 from http://www.emdr.com/general-information/dual-attention-stimuli.html
- EMDR Institute, Inc. Research overview. Retrieved September 1, 2014 from http://www.emdr.com/general-information/research-overview.html
- Shapiro, F. (2001). Eye movement desensitization and reprocessing: Basic principles, protocols, and procedures, second edition. The Guilford Press: New York
 Most of us experience work stress, but can too many responsibilities, unrealistic expectations, and personality conflicts at work lead to an experience of trauma victimization over time?
In my years of private psychotherapy practice, I’ve seen several cases where individuals experience signs similar to posttraumatic stress as a result of work problems. In the beginning, I found this slightly odd. I wondered: could negative work experiences really lead to reactions similar to trauma experiences, like war or sexual assault? Lately, in conversations with colleagues, I’ve discovered this is fairly common, particularly in certain professions.
How Your Work Environment Can Leave You Feeling Victimized
I recently interviewed Arkansas professional counselor Rev. Rebecca Spooner, an ordained minister who left ministry to become a therapist. She specializes in counseling pastors and their families, and said that feeling victimized and traumatized by their work environment is relatively common among members of the clergy. Rev. Spooner explained that the demands and expectations of modern ministry set pastors up for personal failure and emotional trauma.
“The paradigms in ministry are flawed,” Spooner said. “A hundred years ago, pastors had four jobs: marry, bury, baptize, and preach on Sunday. Today, ministers are expected to be marriage therapists and grief counselors, organizational leaders, facilities and staff managers, marketing coordinators, community relations specialists, bloggers, motivational speakers, spiritual teachers, salespeople (increasing membership and giving), budget managers, visit the sick, be a friend, and serve on regional committees! It’s completely unrealistic. It sets everyone up for disappointment.”
[fat_widget_trauma_ptsd_right]
These experiences are similar to what’s happening in private companies in recent times, particularly since the economic crash of 2008. Companies have laid off people and expect those who remain to do more work for less pay. New performance measures are adding pressure, and employees are micromanaged. Among the EAP (Employee Assistance Program) referrals I see in my office, stress related to new and unrealistic work performance expectations ranks at the top of the list.
The people who see me for help with work-related stress have complaints that are similar to what Rev. Spooner sees among clergy: insomnia, irritability, mood swings, anger, feelings of disappointment and disillusionment about their career and employer, confusion about why they are unable to meet the demands placed on them, hopelessness, anxiety and fear, fatigue, muscle tension, family problems, feelings of isolation, ineffective coping, and substance abuse. It’s a long list! Work stress is a big problem in America.
Many of us are familiar with trauma reactions after major catastrophes, but few of us realize that a work environment characterized by unrealistic demands, personality conflicts, and limited free time for leisure can, over time, create an experience of victimization.
3 Ways Cognitive Behavioral Therapy Can Help
Cognitive behavioral therapy (CBT) helps individuals shift from perceiving themselves as having little control over their circumstances to becoming empowered to either change outside pressures or learn to cope with and relate to them differently. With practice, CBT techniques can help reduce stress and anxiety, improve mood, and increase confidence.
CBT treatment has helped ministers reduce the experience of stress and trauma caused by the challenges of their profession. These same techniques can also help most people heal from various traumatic and emotionally difficult situations. CBT reduces distress and helps to restore emotional balance. Here are three techniques from cognitive behavioral therapy to use in your own life.
- Learn to identify the thoughts that increase your anxiety and your self-doubt. A large majority of individuals who come to see me for anxiety therapy are quite surprised when I mention that their thoughts are likely causing their anxiety. Most people believe anxiety is something that happens to them, something over which they have no control. But in fact, how we talk to ourselves about the situations we face has a great deal to do with how we feel. For example, if a minister tells herself that because her church is not growing she is not an effective leader and has failed God, she is likely to feel emotionally upset and believe that she is not capable of growing the church. By repeating self-defeating thoughts in her head, her self-esteem erodes. Eventually, she may just give up trying altogether and become depressed. This is the trick trauma plays on us: it tells us that something is wrong with us and that we are helpless, but most of the time our thoughts are not true.
- Dispute the thought. Once you’ve identified the anxiety-producing or self-defeating thought, it’s time to dispute it. Here’s an example: “If I don’t grow the church, I’ll get fired.” Let’s examine if that thought is true. In most denominations, firing a pastor takes effort. First, the leadership of the church has to vote that they have lost confidence in the pastor. Then, they have to bring the issue to a congregational vote. In many cases, a national mediator becomes involved to help resolve the conflict and improve the employee/employer relationship between the church and the pastor. So the thought, “If I don’t grow the church, I’ll get fired” is not exactly true. What’s much more likely to happen is that if the church is not growing and leaders are dissatisfied, a conversation will occur about why that’s happening. And hopefully, that conversation will lead to solutions. Notice your own thoughts and question them. Are they true? How do you know for sure? What are some alternative explanations that might be more true?
- Learn to relax. The third CBT technique that Rev. Spooner uses is relaxation training. When we learn to relax the tension in our muscles and reduce the speed of our thoughts, our brains function better. They see things more clearly. Gen. Colin Powell has a rule. He tells himself, “It ain’t as bad as you think. It will look better in the morning.” That’s partly because when our brains are rested, we see situations differently. Relaxation training can teach you to rest your brain. My personal hope is that one day, we will collectively learn to be realistic about our demands and expectations of people and be kinder to one another. Until then, if you find yourself feeling victimized, excessively pressured, or doubt your worth or abilities, try CBT. It really can help!